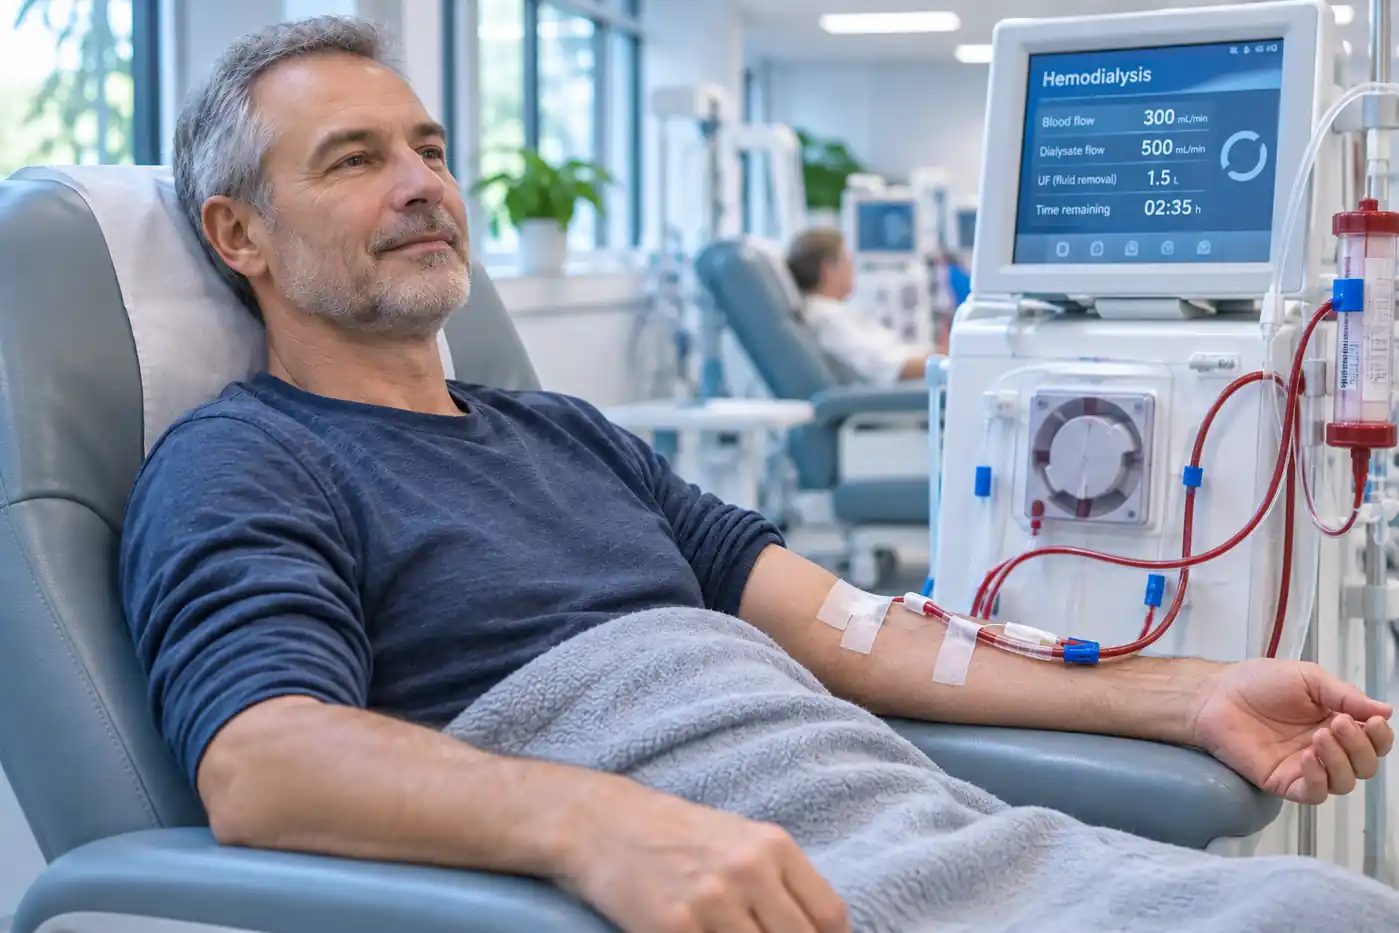
Starting hemodialysis is a major change, and the first appointment can raise practical questions. Will needles be needed? How long does a treatment last? What will the staff monitor, and how might you feel afterward? Knowing the usual sequence can help you prepare, although your own prescription, health and dialysis access determine the details.
Hemodialysis filters blood outside the body using a machine and dialyzer. It helps remove waste products and excess fluid and supports control of electrolytes. This article focuses on the experience of a planned, in-center session. Emergency dialysis and continuous renal replacement therapy used in intensive care follow different protocols.
When a nephrologist may recommend hemodialysis
Hemodialysis may be considered when advanced kidney failure leads to symptoms or laboratory abnormalities that other appropriate measures cannot control. Persistent fluid overload, dangerous potassium levels, acid-base disturbances, severe uremic symptoms or nutritional decline can contribute to the decision. There is no single eGFR result that automatically determines the right start date for every patient.
Before treatment begins, a nephrologist should explain kidney replacement options, including peritoneal dialysis, transplantation and conservative management where appropriate. The discussion includes medical suitability, daily routine, personal preferences and treatment goals. People with an urgent indication may need treatment before every planned preparation step is complete.
Preparing vascular access and your treatment prescription
Hemodialysis needs reliable access to the bloodstream. An arteriovenous fistula joins an artery and vein, while a graft uses a synthetic connection. Both are typically accessed with needles once suitable for use. A central venous catheter connects directly to dialysis tubing and may be used when another access is not ready or appropriate. Access choice depends on the clinical situation, vessel health and timing.
The care team checks your medical history, medicines, allergies, laboratory results and prescribed treatment parameters. They may review bloodborne-infection screening and vaccination needs according to clinical policies. Do not independently stop blood pressure medicines, anticoagulants or diabetes treatment before a session; ask the center for instructions specific to you.
For a person preparing to start dialysis, a nephrology consultation can help clarify whether treatment is indicated, which access is appropriate and how the plan fits with other health conditions. For patients already receiving hemodialysis, the current dialysis prescription and recent session records guide continuity of care.
What happens when you arrive for a dialysis session?
Before the machine is connected
A nurse or dialysis technician commonly checks your weight, blood pressure, recent symptoms and fluid changes since the previous treatment. The team examines the access and confirms the prescription. Pre-treatment weight helps estimate the fluid removal target, but this is individualized. Tell staff about fever, dizziness, new breathlessness, bleeding, access pain, missed medicines or an unexpected change in your condition before treatment starts.
Connecting the dialysis access
With a fistula or graft, trained staff clean the access site and insert dialysis needles. With a catheter, the line is accessed using strict infection-prevention measures. Tubing connects to the machine and dialyzer, where blood passes through a filter before returning to the body. Hand hygiene, proper disinfection and access care are essential because infection can be a serious complication.
During the treatment
The machine controls blood flow and prescribed fluid removal while staff monitor your condition and equipment. Many conventional in-center schedules involve several hours per treatment, often around three sessions per week, but the prescription and schedule can differ. Some people rest, read or talk quietly during treatment. Never shorten a session or change settings on your own, even when you feel well.
How you may feel during treatment and what staff watch for
Some patients feel comfortable throughout treatment; others experience cramps, nausea, headache, tiredness or a drop in blood pressure, particularly when fluid shifts are difficult to tolerate. Tell the team promptly if you feel faint, develop chest discomfort, shortness of breath, fever or unusual pain. Staff can assess whether treatment parameters, medicines or another issue need attention.
The team may review the adequacy of dialysis, blood test trends, fluid balance and access function over time. Hemodialysis as a medical service is more than the machine session: it includes ongoing assessment of kidney failure complications, nutrition, anemia, bone-mineral health and treatment tolerability. More treatment is not automatically better in every circumstance; adjustments must be individualized.
What happens after the machine is disconnected?
After treatment, staff disconnect the tubing, ensure bleeding has stopped at needle sites or properly secure the catheter, and reassess how you feel. Blood pressure and post-treatment weight may be checked. If you feel lightheaded, do not rush to stand or drive until you are safe and the team agrees. Some people are able to resume ordinary activities soon afterward; others need a period of rest.
Protect the vascular access as instructed and observe for redness, swelling, drainage, increasing pain or fever. Report persistent bleeding, loss of the usual vibration over a fistula or other new access changes promptly. Seek urgent care for significant bleeding, chest pain, serious breathing trouble or collapse. Your dialysis team should provide clear advice about whom to contact outside routine session hours.
Hemodialysis, hemodiafiltration and home-based methods
Hemodiafiltration (HDF) combines diffusion and convection to remove certain substances from blood. It is a related treatment, not simply a synonym for routine hemodialysis, and suitability depends on the treating center and medical team. Home hemodialysis may be an option for selected patients after appropriate equipment arrangements and training, but it is not interchangeable with a standard visiting-center appointment.
Peritoneal dialysis works differently by using the lining of the abdominal cavity, with fluid exchanges usually performed by a trained patient or caregiver. Continuous renal replacement therapy (CRRT) is typically used for critically ill patients in hospital intensive care and must not be presented as a travel dialysis service. Decisions about a modality should be made with a nephrologist who understands the person's clinical needs and circumstances.
To compare this procedure with other kidney replacement options, read our dialysis treatment overview. If you already receive dialysis and need sessions during a visit to Croatia, use the dialysis travel planning guide to prepare records and confirm arrangements.
What should you ask before a planned session in Zagreb?
If you are already established on dialysis and need treatment away from your usual center, the questions are different from those of someone who has not started therapy. A receiving center may need your current dialysis prescription, access type, recent blood tests, medicines and previous treatment records before it can assess suitability and availability. Patients considering the start of long-term dialysis should arrange clinical evaluation rather than simply reserving a machine slot.
- What dialysis type and session duration has my nephrologist prescribed?
- What access will be used, and what warning signs must I report?
- What documents and infection-screening results does the receiving center require?
- How will medicines, fluid balance and symptoms be reviewed during the visit?
- Who should I contact if a session is delayed or I become unwell?
ZagrebMed can help with an appropriate nonurgent inquiry for dialysis or nephrology services in Zagreb. The B. Braun Avitum clinic profile provides information on a ZagrebMed dialysis provider, but the clinical team must confirm the individual treatment plan and whether a suitable appointment is available. If you are unwell or require emergency dialysis, seek urgent medical care rather than waiting for an online response.
Medical sources
- NIDDK. Hemodialysis.
- NIDDK. Choosing a Treatment for Kidney Failure.
- CDC. Infections and Patients on Dialysis.
- National Kidney Foundation. Hemodialysis and Hemodialysis Access.
- KDIGO. 2024 Clinical Practice Guideline for Chronic Kidney Disease.
F.A.Q.
Yes. A fistula, graft or catheter provides access to the bloodstream. Your clinical team determines which is suitable and how it is used.
Many conventional sessions last several hours, often around three times per week. Duration and frequency depend on the prescribed treatment.
Needle insertion may cause discomfort. The session itself should not require enduring severe pain. Tell staff immediately about pain or other unexpected symptoms.
Some patients feel well afterward, while others are tired or dizzy. Do not drive if you feel unwell, and follow your care team's individual advice.
Major bleeding, chest pain, serious breathing difficulty or collapse requires urgent care. Fever, access redness or prolonged bleeding should be reported promptly.